WHEN THE BODY LOSES ITS FITRAH
You may have spent years caring for everyone around you — your family, your work, your responsibilities and the people who depend on you. In the name of love and responsibility, it is easy to give away pieces of yourself quietly: your sleep, your time, your energy and sometimes even the attention your own health has been asking for. We rarely notice it happening. Life simply becomes full. Until health changes — and suddenly the ordinary things feel precious again: waking with energy, sleeping peacefully, enjoying a meal, walking without discomfort or making plans without fear.
Cancer makes this truth especially profound. It may begin with abnormal cells and tissues, but its impact rarely stays there. It can change the rhythm of a family, disturb sleep, reshape emotions, challenge confidence and alter the way a person imagines tomorrow. The medical condition may be located in the body, but the experience belongs to the whole human being. Yet illness does not diminish human worth. A person living with spinal cord cancer remains worthy of tenderness, dignity, attention and care. Sometimes, after years of listening to everyone else, illness reminds us to begin listening inward — to our own bodies, too.
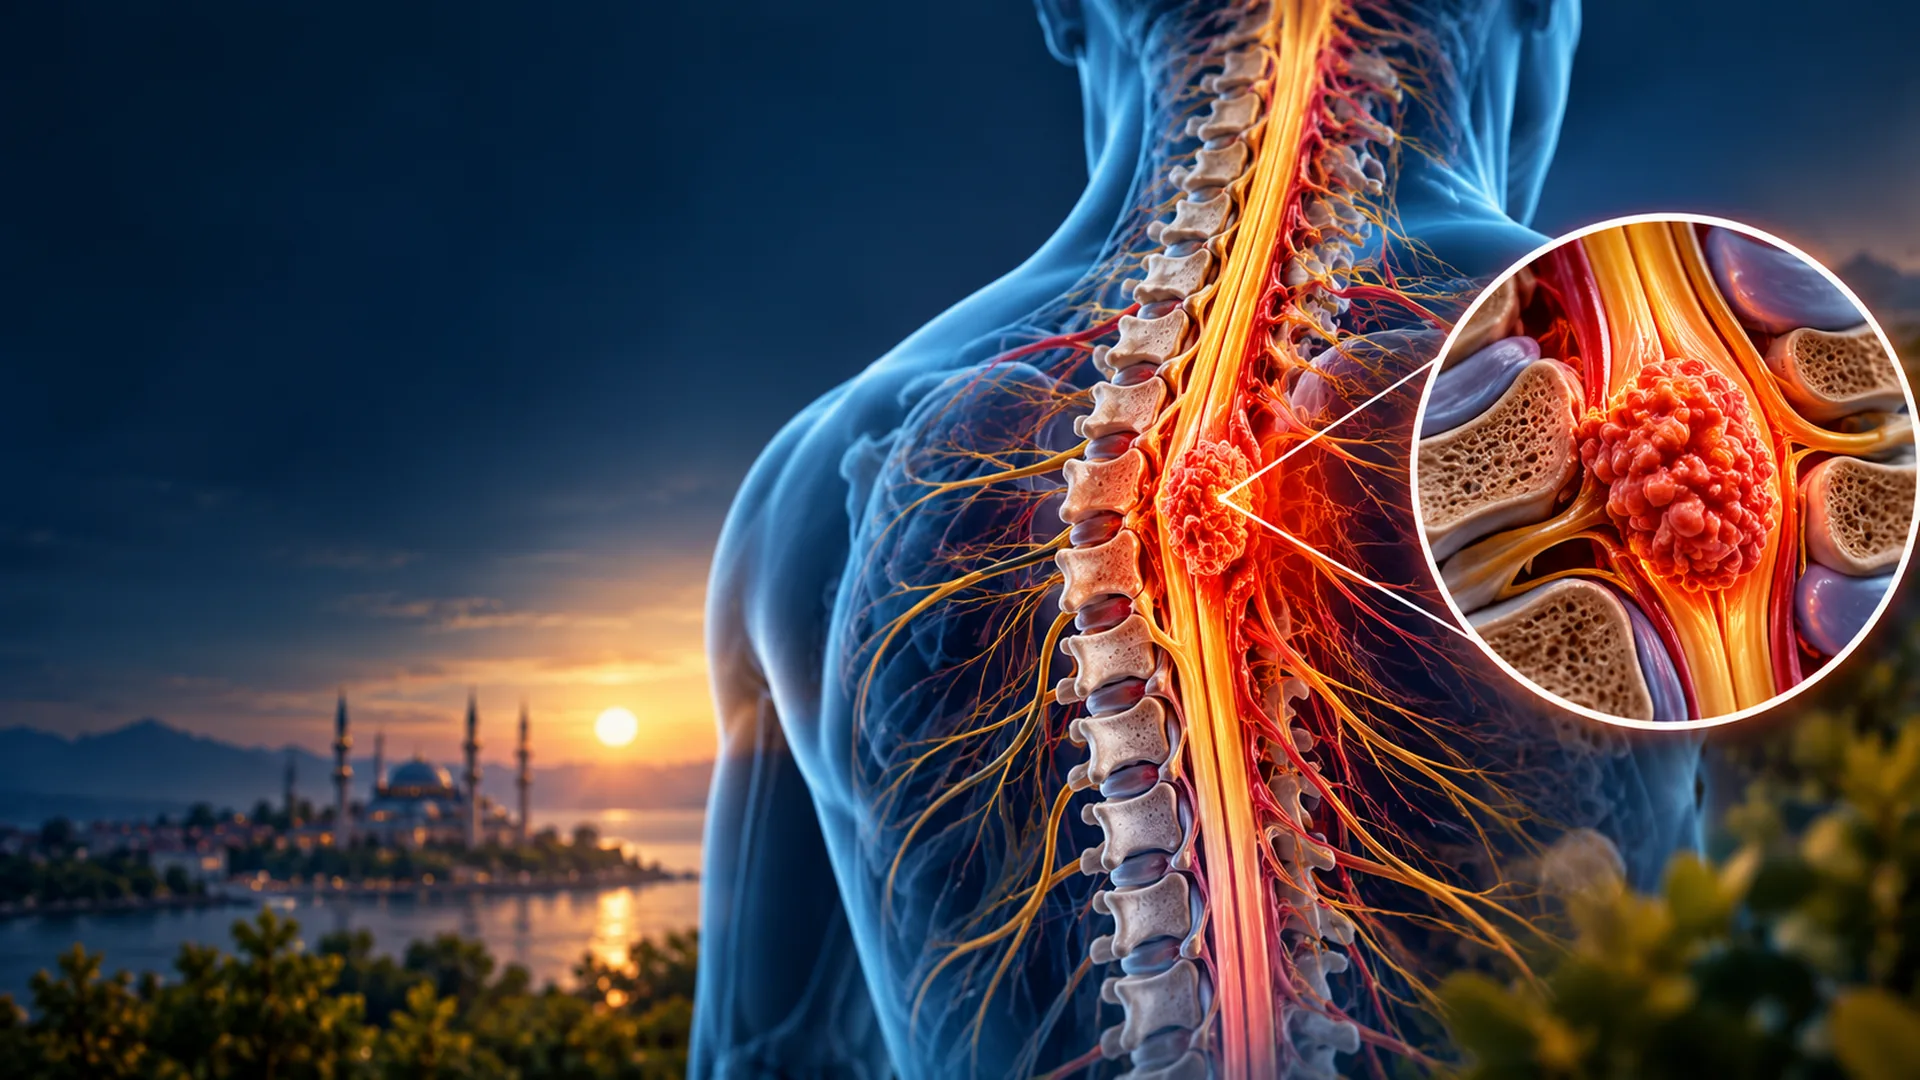
When a tumour affects the spinal cord, these changes can feel especially significant because the spinal cord carries signals between the brain and much of the rest of the body. A person living with spinal cord cancer remains worthy of tenderness, dignity, attention and care.
This leads us to a deeper question: What happens when the natural order that helps the body maintain balance begins to change?
At Ibnu Sina Wellness, this is where we begin looking beyond a single tumour or diagnosis. We model the fundamentals of Ibnu Sina’s medical philosophy through a contemporary whole-person framework that considers the BODY-HEART-MIND-SOUL. [1] The body is not a collection of isolated parts. The human body functions as one connected living system, connected to the environment and way of life.
BUT WHY DOES CANCER OCCUR?
After a cancer diagnosis, one question can become difficult to escape: “Why did this happen?”
Cancer is a complex group of diseases in which abnormal cells can grow beyond their usual boundaries and, in some cancers, invade surrounding tissues or spread to other parts of the body. Cancer develops through interactions between cellular changes and multiple biological, environmental and lifestyle influences. [2] But cells do not live in isolation. Cells also exist within biological environments. They interact with neighbouring cells, blood vessels, immune cells, signalling molecules and the extracellular matrix surrounding them. Inflammation is one example. It is normally part of the body’s protective response. But when inflammatory activity remains active over a prolonged period, it can contribute to tissue dysfunction and biological processes associated with long-term disease, including cancer. [4]
This gives us a more useful way to think about cancer. Cancer is not simply a lump that suddenly appeared. It is a complex disease occurring within an equally complex human body.
And therefore we ask: How do we understand the condition of the whole system rather than looking only at the place where the disease becomes visible?
WHAT MAKES SPINAL CORD CANCER DIFFERENT?
“Spinal cord cancer” is not one single diagnosis.
The spinal cord forms part of the central nervous system and carries information between the brain and the rest of the body. Tumours affecting this area may arise within the spinal cord itself, from nearby structures, or represent disease that has spread from elsewhere. This article focuses primarily on primary tumours arising within the spinal cord, particularly intramedullary spinal cord tumours. Not every spinal cord tumour is malignant. Spinal cord neoplasms are rare, and different tumour types can behave very differently. Important intramedullary tumour groups include ependymal tumours and astrocytic tumours, while other distinct entities can also occur. Some are relatively indolent, while others are malignant and biologically aggressive. [3] [5]
This distinction matters because the word “tumour” does not automatically mean “cancer.” The exact diagnosis depends on the cell type, anatomical location, histological appearance and, increasingly, molecular characteristics. [5] Symptoms can also vary according to where the tumour develops and which spinal pathways are affected. Possible warning signs include persistent or progressive back or neck pain, pain radiating into the arms or legs, numbness, altered sensation, weakness, difficulty walking, balance changes and, in some cases, disturbance of bladder or bowel function. [3] These symptoms can occur in many non-cancerous neurological or musculoskeletal conditions. Persistent, progressive or unexplained neurological changes therefore require appropriate medical assessment rather than self-diagnosis.
Rapidly worsening weakness, difficulty walking, or new bladder or bowel dysfunction requires urgent medical assessment. [3] MRI plays a central role in evaluating spinal cord tumours because it helps define the location, extent and imaging characteristics of a lesion. Imaging can narrow the diagnostic possibilities, but imaging alone may not establish the exact biological diagnosis in every case. Pathological and molecular assessment may be required depending on the tumour and clinical circumstances. [5] [7] Population data also demonstrate how uncommon malignant primary spinal cord tumours are.
A 2024 population-based analysis of more than 5,000 malignant or borderline malignant primary spinal cord tumours in a United States cancer registry showed substantial variation in incidence, histological type and survival according to age and other clinical characteristics. These findings describe a U.S. population and should not automatically be treated as the global pattern. [6] Spinal cord tumours are also not biologically interchangeable. An ependymal tumour should not be treated as though it is an astrocytic tumour. A diffuse midline glioma should not be treated as though it is a conventional spinal ependymoma. A primary intramedullary tumour should not be confused with metastatic cancer involving the spine or spinal canal.
Understanding exactly what tumour is present matters. But the spinal cord still belongs to a living person whose movement, sensation, independence, emotions, relationships, responsibilities and spiritual wellbeing continue alongside the diagnosis. The tumour matters. But so does the person living through everything around it.
WHAT DID IBNU SINA UNDERSTAND ABOUT HEALTH AND DISEASE?
Ibnu Sina — also known as Avicenna — wrote more than 450 books including Al-Qanun fi al-Tibb, or The Canon of Medicine. His medical writings reflected the knowledge and medical framework beyond his historical period, including the humoral theory — a model that explained health through the balance of bodily humours or fluids. [8] An important principle within Ibnu Sina’s medical reasoning remains deeply relevant to the philosophy of Ibnu Sina Wellness: do not understand one part of ailment without understanding the condition of the whole person. [1] At Ibnu Sina Wellness, we have taken inspiration from this whole-person orientation and developed it into a contemporary framework.
The disease may appear in one part of the body, but the person experiencing it is always more than that one part.
IBNU SINA WELLNESS — MODELING THE FUNDAMENTALS OF IBNU SINA MEDICINE
Ibnu Sina Wellness was established in 2015 in Kajang, Selangor, Malaysia. Since then, our work has focused on bringing whole-person principles into a structured wellness model. We have served people from Malaysia, Singapore, Indonesia and Brunei, including people living with complex and long-standing health challenges.
Through that experience, one principle has remained central to our philosophy: We do not reduce a person to a diagnosis. We want to understand the whole human being.
THE BPS-S LENS VIEWS THE PERSON BEHIND THE DIAGNOSIS
This is where the Biopsychosocial-Spiritual, or BPS-S, framework becomes especially important. BPS-S recognises that human health and illness are experienced across interconnected biological, psychological, social and spiritual dimensions. These dimensions do not exist as separate compartments. They belong to one human life. [1] For someone living with a spinal cord tumour or cancer, the biological dimension includes the exact tumour type and location, pain, strength, sensation, balance, walking, bladder and bowel function, nutrition, sleep, treatment effects, rehabilitation and recovery needs. The psychological dimension may include fear, uncertainty, concern about disability, anxiety about surgery or recurrence, frustration with physical limitations and concern about losing independence.
The social dimension may include relationships, employment, caregiving roles, finances, transport, accessibility, rehabilitation needs and practical changes to everyday life. The spiritual dimension includes meaning, hope, purpose, relationship with Allah and the way a person understands illness within the wider journey of life. These dimensions interact. Whole-person care therefore creates space to understand not only the biological condition, but also what the person is carrying emotionally, socially and spiritually. [9] Weakness may affect employment. Difficulty walking can change family roles and independence. Neurological symptoms may alter sleep and confidence. Rehabilitation can become part of everyday life long after surgery.
Research examining adults who underwent surgery for intramedullary spinal cord tumours found that neurological and functional difficulties can continue to influence quality of life over the long term. Pain, disability and physical limitations may remain important even years after treatment. [10] This evidence relates specifically to surgically treated adults with intramedullary spinal cord tumours and should not be generalised to every spinal tumour, every treatment pathway or every patient. A diagnosis tells us what disease is present. It does not tell us everything the person is carrying. To care for the person well, we must first learn to see the person as a whole.

AT IBNU SINA WELLNESS, WE DO NOT LOOK AT ONLY ONE DISEASE
When someone comes to us with spinal cord cancer, we do not want to see only the words written on a medical report. We want to see: THE WHOLE PERSON.
Within the Ibnu Sina Wellness functional framework, body functions are mapped across:
12 MAJOR BODY SYSTEMS
and
120 MICRO-SYSTEMS.
The 120 Micro-Systems are an Ibnu Sina Wellness functional framework. They give our practitioners and educators a more detailed way of asking: “Where is the body’s function giving us a signal?” Instead of seeing one tumour in one location, we look at the interconnected network supporting the person.
THE 12 SYSTEMS ARE NOT 12 SEPARATE MACHINES
The human body is made up of systems with different responsibilities, but they do not function like twelve separate machines. The nervous system communicates and coordinates. The endocrine system regulates through hormones. The cardiovascular system circulates blood, oxygen and nutrients, while the respiratory system performs the essential exchange of gases. The digestive system processes and absorbs what we eat, the liver carries out vital metabolic and processing functions, and the urinary system regulates fluids while eliminating metabolic waste. [11]
The same interdependence continues throughout the body. The immune system protects and monitors, the lymphatic system supports immune function and fluid balance, the musculoskeletal system provides structure and movement, the integumentary system — the skin, hair, nails and associated structures — protects the body while interacting with the external environment, and the reproductive system carries reproductive and hormonal functions. [11] The spinal cord demonstrates interconnection especially clearly. Signals travelling through the spinal cord help coordinate movement, sensation and communication between the brain and much of the body. Motor pathways influence muscles, while sensory pathways transmit information involving touch, pain, temperature and body position. [11]
The spinal cord also participates in neural pathways involved in bladder, bowel and autonomic function. But it cannot perform these roles independently. A change within the spinal cord can therefore be experienced far beyond the precise anatomical location of a tumour. But none of these systems operates independently. Hormones travel through the circulation. The lungs and cardiovascular system work together to deliver oxygen. The kidneys regulate fluids and electrolytes. The nervous and endocrine systems coordinate countless processes throughout the body. [11] The body works through connection. And that is why understanding one part often requires us to look at the system surrounding it.
THE 120 MICRO-SYSTEMS AS CHECKPOINTS
This is where our 120 Micro-Systems become particularly important. Rather than beginning only with the question, “What disease do you have?”, we begin by looking more closely at the signals the body is giving us. Which system is signalling that something has changed? Which micro-system may be involved? What function is being affected? What may be disturbing that function? And what root-cause factors may need to be explored?
This creates a pathway for deeper investigation:
Symptom → System → Micro-System → Function → Imbalance → Root-Cause Factors → Restoration of Balance
The purpose is to move beyond naming the symptom and stopping there. A symptom can tell us where to begin looking, but it does not necessarily tell us the whole story. The symptom is not the end of the investigation. It is the beginning.
WHY THE MICRO-SYSTEM CANNOT BE SEPARATED FROM THE WHOLE PERSON
There is another principle that is essential: a micro-system does not exist separately from the life of the person experiencing the problem. A biological function may be under strain, while the same person may also be experiencing fear, anxiety, grief, anger, uncertainty, disturbed sleep, changes in relationships, loss of confidence, caregiving demands or spiritual distress. The BPS-S perspective helps us understand how these dimensions exist within the same life. What happens in the body is experienced by a person who also has emotions, thoughts, relationships, responsibilities and a spiritual life. [1]
So when we say “we look at the micro-system,” we are not looking only at biology. We are also asking what is happening emotionally and mentally, what is happening within relationships and circumstances, and what is happening within the spiritual dimension of life. Because these are not separate human beings. They are dimensions of one human life. And that is why understanding the micro-system must always lead us back to understanding the whole person.
THE MICRO-SYSTEM IS A BIOLOGICAL CHECKPOINT — BUT THE PERSON IS MORE THAN BIOLOGY
Imagine a city. You cannot understand its condition by looking at one building alone. Roads, water systems, electricity, communication networks, transportation, waste management, security and emergency services all depend upon smaller functions working together. The human body is far more complex. Every major system contains specialised functions, and those functions continuously interact with others. But the human being adds another layer: the person living inside that body has emotions, thoughts, relationships, memories, responsibilities, values and a spiritual life. [9] The spinal cord works within an even more complex living network. A tumour in one region may affect movement. Another may change sensation. Another may interfere with walking or bladder and bowel control.
The physical condition is real. But so is the person experiencing it. A biological checkpoint can help us understand what is happening within the body, but it can never describe the whole human being.
WHAT DOES “TOXIC BURDEN” MEAN AT IBNU SINA WELLNESS?
One of the concepts we investigate at Ibnu Sina Wellness is toxic burden. This can include harmful exposures associated with cancer risk, such as tobacco smoke, alcohol, air pollution, ultraviolet and ionising radiation, cancer-causing infections and particular occupational or environmental carcinogens. [2] [12] We also look at the wider metabolic and lifestyle environment surrounding the individual. Excess body weight, physical inactivity and patterns of nutrition are among the modifiable factors studied in relation to cancer risk, while chronic inflammation forms part of the wider biological environment relevant to disease. [4] [12]
Sleep and prolonged stress matter here for a different but equally human reason. They shape the way a person functions, copes and moves through illness, and therefore belong within the wider whole-person picture. [1] [10] This can include harmful exposures associated with cancer risk generally, such as tobacco smoke, alcohol, air pollution, ultraviolet and ionising radiation, cancer-causing infections and particular occupational or environmental carcinogens. [2] [12] For primary spinal cord tumours, however, scientific precision is especially important. There is no single toxic-burden pattern known to explain the different primary tumours that arise within the spinal cord.
General cancer risk factors should therefore not automatically be presented as established causes of spinal ependymoma, spinal astrocytoma, diffuse midline glioma or every other spinal cord tumour. Certain tumour types do have specific molecular or predisposition contexts. For example, NF2-related schwannomatosis, historically known as neurofibromatosis type 2, is associated with some spinal ependymal tumours, while modern classification also recognises molecularly distinct spinal ependymoma subgroups, including rare tumours characterised by MYCN amplification. [13] These findings belong to specific biological contexts. They do not mean that most people with spinal cord cancer have an inherited syndrome, and genetic predisposition is not a toxin.
Sleep and prolonged stress matter for wellbeing and coping, but they should not be presented as proven causes of primary spinal cord cancer. [1] Toxic burden is therefore not one mysterious substance or one universal explanation for cancer. It is a way of examining potentially harmful exposures and modifiable burdens while keeping established disease biology, general health factors and the lived experience of illness scientifically distinct. At Ibnu Sina Wellness, we bring these pieces together to understand the wider pattern of exposures, physiological demands and modifiable burdens surrounding the person.
The body does not experience life as a list of separate risk factors. It experiences the pattern created by them over time. Toxic burden is therefore not one substance. It is the cumulative pattern of what the body has repeatedly been asked to process, tolerate and adapt to over time.

THE BIOLOGICAL BURDEN AND THE EMOTIONAL-MENTAL-SOUL BURDEN
A person may carry biological burdens while also carrying grief, fear, anger, betrayal, loneliness or unresolved emotional pain. The mind can carry its own burden too — constant worrying, overthinking, perfectionism, self-criticism, uncertainty or feeling that one must always remain strong. Daily life may add another layer through caregiving responsibilities, financial pressure, relationship conflict, work demands and long periods of uncertainty. There is also the spiritual dimension. A person may struggle with meaning, hope, spiritual connection, trust in Allah or the feeling that life has lost its direction. Spiritual distress has also been described among people living with cancer. [15]
A person may carry biological burdens alongside fear, grief, loneliness, uncertainty, overthinking, self-criticism, caregiving demands, financial pressure or relationship strain. Spinal cord tumours can create particular emotional and practical challenges because neurological function and independence may become part of the illness experience. A person may worry about whether they will continue walking normally, whether weakness will progress, whether bladder or bowel function will change, whether surgery will affect neurological function or how much rehabilitation may be needed. These experiences matter. But they should not be presented as biological causes of the tumour.
There is also the spiritual dimension. A person may struggle with meaning, hope, spiritual connection or trust in Allah. Spiritual distress has been described among people living with cancer. [15] These experiences can shape how a person lives through illness, but they do not establish why a spinal cord tumour developed. This is why the BPS-S perspective matters. The biology matters. But so do the heart, the mind, the life surrounding the person, and the soul.
OVERHAUL BODY™ — SUPPORTS THE WHOLE SYSTEM
This is where Overhaul Body™ fits into the Ibnu Sina Wellness philosophy. Overhaul Body™ is designed as a whole-person journey that looks beyond the tumour to the wider person and the interconnected systems supporting them. Ibnu Sina Wellness offers a new era in cancer healthcare — without chemotherapy, without surgery, without radiation, and without machine-based treatment. Within ISW, its Recovery Plan is structured around 15 integrated methods spanning herbal medicine, mind, natural lifestyle and spiritual care. This reflects the wider Ibnu Sina Wellness whole-person philosophy, which brings together the body, heart, mind and soul and incorporates approaches such as herbal remedies, natural lifestyle practices, nutrition and spiritual care. [1]
This wider supportive view also aligns with the field of integrative oncology, where supportive approaches may be considered alongside cancer-directed care. [17] Within the ISW framework, support begins by strengthening foundations such as nutrition, appropriate movement, bowel movement, sleep, rest and recovery, emotional wellbeing, mental wellbeing and spiritual wellbeing. This describes the Ibnu Sina Wellness supportive whole-person programme. It should not be interpreted as evidence that a wellness programme replaces medically indicated treatment for a malignant spinal cord tumour. Diagnosis, imaging, pathological and molecular classification, assessment of tumour extent and cancer-directed management require appropriate specialist medical care.
Treatment differs according to the exact tumour type, grade, location, molecular features and neurological circumstances. Surgery is an important treatment for many intramedullary spinal cord tumours when appropriate, while radiotherapy, chemotherapy or targeted approaches may have roles in selected tumour types or clinical situations. These approaches cannot be generalised across every spinal cord tumour because biological behaviour and treatment sensitivity differ substantially among subtypes. [3] [5] Management therefore requires appropriate multidisciplinary neurological, neurosurgical, pathological, oncological and rehabilitation expertise according to the individual case. Tissue repair involves coordinated interactions among cells, signalling molecules and the extracellular matrix as damaged tissues move towards restoration. [16]
These are normal biological processes. Normal physiology itself depends on ongoing processes of regulation and repair. Homeostasis describes the body’s continuous regulation of its internal environment. [11] Tissue repair involves coordinated interactions among cells, signalling molecules and the extracellular matrix as damaged tissue moves towards restoration. [16]
These processes remind us of something important: The body is constantly working to regulate, communicate and repair. Our role is to support the person living within that body. And ultimately, the aim of Overhaul Body™ is to support the whole person.
We support the body.
We support the person.
And we leave healing ultimately to Allah.
WHAT DOES “UNLOAD” MEAN?
When we say Overhaul Body™ aims to unload harmful burdens, we mean addressing factors that can reasonably be changed. This may include reducing avoidable harmful exposures, improving nutrition, supporting bowel movement and normal elimination, improving sleep, encouraging appropriate movement, creating space for rest and recovery and addressing emotional, mental and spiritual burdens. For someone with spinal cord cancer, this does not mean claiming that every burden caused the tumour or that removing a burden will remove malignant spinal cord cells. Cancer-directed medical care addresses the malignancy itself.
Sometimes support begins not by adding more, but by asking: What can reasonably be reduced?
Because our framework contains 120 Micro-Systems, we can then ask more focused questions: Which functions need attention? Which systems are under strain? Which burdens may be modifiable? What does this person need biologically, psychologically, socially and spiritually? Unloading, in this sense, is about making room for the body and the person to function with less unnecessary burden.
BUT WHAT ABOUT THE CANCER CELL?
Cancer cells involve complex biological changes. They may grow abnormally, escape normal growth controls, interact with surrounding tissue and, in some cancers, invade nearby tissue or spread to other parts of the body. [2] [3] Primary spinal cord tumours involve different cells and different molecular pathways depending on the tumour type. Modern classification has changed the way several ependymal and glial tumours are understood because molecular characteristics now help distinguish biologically meaningful tumour groups that cannot be defined by location or microscopic appearance alone. [5] [13] Spinal ependymal tumours provide one example.
Recent molecular research has identified differences among spinal ependymal tumour subgroups, including differences in gene-expression patterns and immune-related pathways. A 2025 multi-omics study comparing several spinal ependymal tumour groups found distinct molecular signatures and differences in pathways related to the tumour environment. [14] But this evidence requires careful interpretation. The study was a relatively small, single-centre investigation and focused specifically on spinal ependymal tumours. Its findings should not be generalised to astrocytoma, diffuse midline glioma or every spinal cord malignancy. Nor should exploratory molecular or immune findings be interpreted as established treatment benefit.
This biology remains important within whole-person care. Within the ISW framework, Overhaul Body™ focuses on supporting the person and the interconnected systems surrounding that biological challenge, while strengthening modifiable foundations across the wider health journey. [1] The cancer cell remains important. But it is not the whole story.
THE LAW OF FITRAH
At Ibnu Sina Wellness, we describe this wider natural order through Fitrah. Fitrah refers to the natural disposition and order created by Allah. Within the ISW BPS-S model, this provides a wider spiritual lens through which health, balance and the human being are understood. [1] At the biological level, the body demonstrates remarkable processes of regulation and repair. When tissues are injured, repair involves coordinated interactions among cells, signalling molecules and the extracellular matrix — the structural material surrounding cells — as the tissue works towards restoration. [16] The body also continuously regulates temperature, blood glucose, fluid and electrolyte balance, acidity and many other internal conditions.
Physiology describes this maintenance of internal stability as homeostasis — the body’s ability to maintain an internal environment compatible with normal function despite changing conditions. [11] At the biological level, the spinal cord demonstrates extraordinary organisation. When tissues are injured, repair involves coordinated interactions among cells, signalling molecules and the extracellular matrix. [16] These are biological processes. Within the ISW framework, Fitrah gives this natural order a wider meaning. It invites us to recognise that the human body is not merely a machine. It is a living system created with extraordinary organisation by the Almighty Creator.
Our responsibility is to support that order as best we can.

THE WHOLE PERSON — NOT ONLY THE CANCER
This brings us to one of the most important principles at Ibnu Sina Wellness: We do not only look at the disease.
We look at the body — the physical body and its systems.
We look at the heart — emotional wellbeing and the experiences carried within us.
We look at the mind — thoughts, perceptions, beliefs and patterns of thinking.
And we look at the soul — meaning, purpose, relationship with Allah and spiritual wellbeing.
At the same time, the BPS-S lens reminds us to understand the biological, psychological, social and spiritual dimensions together. [1] Within the body, we look across the 12 body systems and the 120 Micro-Systems as functional checkpoints. This gives us a much richer question than simply asking: “What disease do you have?”
We ask: What is your body telling us? Which system is giving the signal? Which functional micro-system may be involved? What is affecting its function? What biological burdens are present? What emotional and mental burdens are present? What is happening in the person’s relationships and circumstances? What is happening in the person’s life and soul?
And ultimately: What do we need to understand about the whole you?
COME AND HEAL “ALL” PARTS OF YOU
If you are living with a malignant spinal cord tumour and do not know what to do, if you have completed treatment and are living with fear that it may return, or if persistent back pain, progressive weakness, numbness, walking difficulties or unexplained bladder or bowel changes are worrying you, perhaps what you need is a place where people see more than the diagnosis. Come and speak with our professionals. At Ibnu Sina Wellness, established in 2015 in Kajang, Selangor, we welcome you as a whole person. Our multidisciplinary team includes Hakeema, Hakeem, medical doctors, nutrition professionals, physiotherapists and counsellors, working within the broader whole-person philosophy of Ibnu Sina Wellness.
We want to understand your history, your body, your systems and your 120 functional Micro-Systems. We want to understand your nutrition, movement, bowel movement and sleep, as well as your emotional wellbeing, mental patterns, life circumstances and spiritual wellbeing. We want to understand the person behind the diagnosis. Because what you need now is not another person simply telling you what is wrong with you.
We will sit with you to understand the whole you and ask:
What has happened to you?
What is your body telling us?
Which systems need attention?
Which burdens can we reduce?
How can we support your 120 Micro-Systems?
And how can we help you move towards greater balance and Fitrah?
For a consultation, kindly call Ibnu Sina Wellness at 03-604 30663. You may also join Ibnu Sina Wellness Official on TikTok LIVE for general guidance and transform your perspective on daily life issues. You deserve to be cared for as a whole human being. You deserve compassion, dignity and the opportunity to be heard. And you deserve support for the body, heart, mind and soul that have carried you this far. May Allah grant you wellbeing, strengthen your body, calm your heart, illuminate your mind, strengthen your soul and guide you towards what is best for you.
HAKEEMA ROZAINAH
Founder & CEO of Ibnu Sina Wellness
Registered Practitioner with Ministry of Health Malaysia (Act 775 Traditional and Complementary Medicine)
Pioneer of WHO’s Biopsychosocial- spiritual medicine in Malaysia
Specializing in Ibn Sina Medicine, with a focus on herbal therapy for cancer management
Understanding the Whole Person. Discovering the Root. Supporting the Systems. Caring for the 120 Micro-Systems. Returning Towards Fitrah.
REFERENCES
1. Hakeema Rozainah, & Prof. Dato Sri Dr. Abu Hassan Asaari. (2025). Biopsychosocial-Spiritual: A New Era in Healthcare. ISW Media Sdn. Bhd.
2. World Health Organization. (2023). Cancer fact sheets.
3. McFaline-Figueroa JR. Spinal Cord Neoplasms. Continuum (Minneap Minn). 2024;30(1):99–118. doi:10.1212/CON.0000000000001375.
4. Furman D, Campisi J, Verdin E, et al. Chronic inflammation in the etiology of disease across the life span. Nature Medicine. 2019;25(12):1822–1832. doi:10.1038/s41591-019-0675-0.
5. Esparragosa Vazquez I, Ducray F. The Role of Radiotherapy, Chemotherapy, and Targeted Therapies in Adult Intramedullary Spinal Cord Tumors. Cancers. 2024;16(16):2781. doi:10.3390/cancers16162781.
6. Liu H, Duan L, Li Z, Liu Y, Wang Y. Incidence and Survival of Patients With Malignant Primary Spinal Cord Tumors: A Population-Based Analysis. Neurospine. 2024;21(2):588–595. doi:10.14245/ns.2347300.650.
7. Shah LM, Salzman KL. Conventional and Advanced Imaging of Spinal Cord Tumors. Neuroimaging Clinics of North America. 2023;33(3):389–406. doi:10.1016/j.nic.2023.03.001.
8. Retsas S. Perceptions of Cancer Through the Ages—From Hippocratic Oncology to Precision Cancer Medicine. Biomolecules. 2024;14(11):1383. doi:10.3390/biom14111383.
9. Lynch JM, van Driel M, Meredith P, Stange KC, Getz L, Reeve J, Miller WL, Dowrick C. The Craft of Generalism: Clinical skills and attitudes for whole person care. Journal of Evaluation in Clinical Practice. 2022;28(6):1187–1194. doi:10.1111/jep.13624.
10. Tufo T, Grande E, Bevacqua G, Di Muccio I, Cioni B, Meglio M, Ciavarro M. Long-term quality of life and functional outcomes in adults surgically treated for intramedullary spinal cord tumor. Frontiers in Psychology. 2023;14:1136223. doi:10.3389/fpsyg.2023.1136223.
11. Hall JE, Hall ME. Guyton and Hall Textbook of Medical Physiology. 14th ed. Elsevier; 2021.
12. Islami F, Marlow EC, Thomson B, McCullough ML, Rumgay H, Gapstur SM, Patel AV, Soerjomataram I, Jemal A. Proportion and number of cancer cases and deaths attributable to potentially modifiable risk factors in the United States, 2019. CA: A Cancer Journal for Clinicians. 2024;74(5):405–432. doi:10.3322/caac.21858.
13. Kresbach C, Neyazi S, Schüller U. Updates in the classification of ependymal neoplasms: The 2021 WHO Classification and beyond. Brain Pathology. 2022;32(4). doi:10.1111/bpa.13068.
14. Liu W, Ning C, Geng X, et al. Multi-omics analysis delineates molecular signatures of spinal ependymal tumor. Cellular Oncology. 2025;48(6):1987–2000. doi:10.1007/s13402-025-01122-0.
15. Farahani AS, Kerdar SH, Ashrafizadeh H, Büssing A, Mehrnoush N, Akbari ME, Karami M, Tajalli S, Mojen LK, Rassouli M. The predictors of spiritual dryness among Iranian cancer patients during the COVID-19 pandemic. Frontiers in Psychology. 2023;13:1024009. doi:10.3389/fpsyg.2022.1024009.
16. Krafts KP. Tissue repair: The hidden drama. Organogenesis. 2010;6(4):225–233. doi:10.4161/org.6.4.12555.
17. Fuller-Shavel N, Krell J. Integrative Oncology Approaches to Supporting Immune Checkpoint Inhibitor Treatment of Solid Tumours. Current Oncology Reports. 2024;26(2):164–174. doi:10.1007/s11912-023-01492-4.
October 28, 2026